Border closures and forced 21-day isolation periods look fantastic in political press releases. They reassure a panicked public that the state is "taking decisive action" against a terrifying hemorrhagic fever.
There is only one problem: in epidemiology, reactionary forced quarantines are worse than useless. They actively spread disease.
Uganda’s mandate forcing travelers returning from the Democratic Republic of Congo into a three-week state-run quarantine is a textbook case of public health security theater. It is a political reflex masquerading as sound medical protocol. Bureaucracy loves a blunt instrument, but infectious disease control requires a scalpel. When you force human beings into arbitrary, heavy-handed confinement along porous, highly fluid international borders, you do not stop a virus. You drive it underground.
The Fatal Flaw of Border Isolation Protocols
Public health authorities routinely fall into the trap of managing optics instead of mechanics. The logic seems simple enough to the average bureaucrat: keep the infected people on that side of the river, put anyone who crosses into a holding pen for 21 days, and the risk vanishes.
It sounds airtight until you factor in actual human behavior.
I have spent years observing public health interventions in high-density, low-resource corridors across Sub-Saharan Africa. The moment a state announces compulsory, state-funded or self-funded isolation at border checkpoints, cross-border traffic does not halt. It simply shifts half a mile down the river, away from official border agents, medical monitors, and temperature scanners.
Border communities along the DRC-Uganda frontier do not view the border the way policy analysts in Kampala or Geneva do. To them, the border is an arbitrary line drawn on a map. Families live on both sides. Trade happens daily. Small-scale vendors cross multiple times a week to sell produce, fuel, and textiles.
When you attach a 21-day forced isolation penalty to legal transit, you incentivize every single person with a low-grade fever, a headache, or a financial necessity to bypass official entry points entirely.
Instead of screening 10,000 people a day at a equipped checkpoint with trained healthcare workers, you screen 1,000, while 9,000 walk through unmonitored footpaths through the bush. You haven't constructed a containment wall. You've intentionally blinded your own surveillance network.
The Physical Risk of Mass Holding Facilities
Let us look at the mechanics of state-run quarantine centers.
When you place hundreds of individuals—some who have Ebola, some who have malaria, some who have typhoid, and many who are completely healthy—into crowded transit facilities, you create a perfect incubation engine.
Ebola is not airborne, but it spreads rapidly through direct contact with body fluids, contaminated bedding, and shared sanitation facilities. The early symptoms of Ebola virus disease (EVD) are completely non-specific:
- Sudden onset of high fever
- Muscle aches and joint pain
- Severe head pain
- Extreme fatigue and weakness
- Sore throat
These initial signs match the exact clinical presentation of severe Plasmodium falciparum malaria, which affects tens of millions of people in the Great Lakes region every year.
If a traveler returning from Beni or Butembo develops a high fever on day three of a forced border quarantine, what happens? In an ideal world, they are instantly isolated in a negative-pressure room with trained personal protective equipment (PPE) staff. In reality, in border facility holding pens, that individual shares a latrine, a water point, and a waiting area with dozens of uninfected travelers for hours—or days—while lab samples are routed to a central laboratory in Entebbe or Kampala.
By turning border checkpoints into holding camps, you guarantee that individuals who entered the facility uninfected are exposed to those in the early, highly infectious stages of viral shedding. You literally create the outbreak you set out to prevent.
The Math of incubation vs. The Reality of Economics
Why 21 days? Because 21 days represents the maximum theoretical incubation window for the Ebola virus. The World Health Organization (WHO) has long established that the incubation period ranges from 2 to 21 days, though the mean incubation period sits between 8 and 12 days.
Twenty-one days sounds scientifically bulletproof. Financially and socially, it is a death sentence for informal traders.
Imagine a mother crossing from Eastern Congo to market hubs in western Uganda to sell goods that feed her family for the week. A mandatory three-week quarantine strips away her entire livelihood in a single afternoon. She cannot afford 21 days of lost income, nor can she pay for basic sustenance inside poor facility conditions.
When public health mandates demand that individuals choose between potential viral exposure and guaranteed economic destruction, economic survival wins every single time.
People will falsify travel histories. They will bribe border officials. They will dodge health monitors. They will take dangerous river crossings at night.
By demanding total compliance through crude mandates, public health agencies lose the trust of the populations they need most. Trust is the single most critical currency in epidemic control. Lose it, and no amount of thermal cameras or armed border guards will save you.
What Actually Works: Ring Vaccination and Community Surveillance
If forced 21-day border quarantines are a failure of logic, how do you actually contain a hemorrhagic fever outbreak across a fluid border?
You do it by abandoning political theater in favor of proven, hyper-targeted epidemiologic interventions.
1. Decentralized Ring Vaccination
During the West Africa Ebola outbreak (2014-2016) and subsequent outbreaks in the DRC, the deployment of the rVSV-ZEBOV vaccine proved that targeted containment works. Rather than locking down entire transit corridors, health authorities must deploy "ring vaccination" strategies immediately:
- Identify every primary contact of a confirmed case.
- Vaccinate those contacts, along with their secondary contacts (their "ring").
- Vaccinate all frontline border officials, healthcare workers, and informal transport operators (boda-boda drivers) along key transit routes.
Vaccinating the human wall around the virus creates an immunological barrier that stops transmission without requiring draconian population lockups.
2. Voluntary Self-Monitoring with Financial Safety Nets
Instead of forcing returning citizens into overcrowded quarantine camps, deploy contact-tracing technology combined with direct cash transfers.
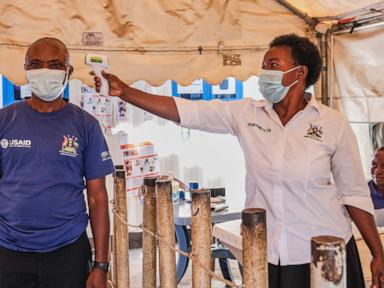
When a traveler crosses an official border post, register their phone number, verify their destination address, provide them with a digital thermometer, and pay them a daily stipend to stay home and report their daily temperature via SMS or USSD code.
If they develop a fever, a mobile medical team equipped with rapid diagnostics comes directly to them. Because they are not threatened with forced institutionalization or loss of income, their incentive to report early symptoms skyrockets. Early detection means early isolation before community transmission occurs.
3. Deep Integration with Community Leaders
Epidemic response fails the moment it feels like an military occupation. Border monitoring must be led by local village health teams, market organizers, and border community leaders who understand the daily movement of people. When local leaders enforce health monitoring, compliance rises. When armed guards demand compliance under threat of detention, compliance vanishes.
The High Cost of Easy Answers
It is easy to see why politicians keep defaulting to the 21-day quarantine model. It looks strong. It makes for authoritative headlines. It shifts the blame onto "outside forces" crossing the border.
But public health policy cannot be evaluated on intent; it must be judged exclusively on outcomes.
Every time a government deploys forced border detentions, it signals to its population that honesty will be punished. It guarantees that the next infected person who crosses the border will do so in the dark, will avoid medical facilities when their symptoms begin, and will infect their family and neighbors before anyone in authority even knows they exist.
Stop relying on epidemiological theater. Tear down the border holding pens, fund community-based surveillance, incentivize voluntary self-reporting, and deploy vaccines to the front lines. Anything less isn't disease control—it is a disaster waiting to happen.